
What Does a Personalized Cancer Vaccine Really Cost Per Patient?
There is still no audited public answer.
Most personalized cancer vaccines remain investigational, and developers rarely disclose complete patient-level cost of goods. Public discussions also mix together different numbers: laboratory cost, internal manufacturing cost, a CDMO quotation, clinical-trial spending and the eventual commercial treatment price. A defensible estimate therefore has to define its scope before assigning a number—and label modeled assumptions as assumptions.
The cost begins before manufacturing
A personalized vaccine normally starts with tumor tissue and a matched normal sample. Pathology must confirm that the specimen is adequate before whole-exome sequencing, tumor RNA sequencing and HLA typing can support neoantigen selection. As a research-price reference, MD Anderson lists 100x whole-exome sequencing at US$715 per sample and tumor RNA sequencing at US$850. A tumor-normal WES pair plus tumor RNA would therefore total about US$2,280 before pathology, HLA testing, validated analysis or scientific review. [1]
The bioinformatics stage is not simply an algorithmic prediction. It includes variant calling, expression analysis, candidate ranking, quality control and expert review. These upstream activities are important to total treatment economics, but they are excluded from the manufacturing estimate below.
What a bottom-up manufacturing model suggests
For an individualized mRNA-LNP vaccine, we built a bottom-up scenario model of the manufacturing-and-release cost of producing one patient-specific lot sufficient for the planned treatment course. The scope runs from a finalized patient-specific sequence through released, packaged product and dispatch to the clinic. This is not a machine-learning forecast. The model adds the DNA template, GMP IVT inputs, LNP formulation, fill-finish, QC and batch release, manufacturing and QA labor, facility allocation, cold-chain dispatch and an allowance for failed or repeated batches.
The central scenario produces approximately US$230,000 per successfully released patient course in the United States and US$130,000 in China, equivalent to roughly RMB0.86 million at the model exchange rate of RMB6.75 per U.S. dollar. Because the evidence is incomplete, the ranges are more important than the point estimates. They are scenario bounds, not statistical confidence intervals. [6]
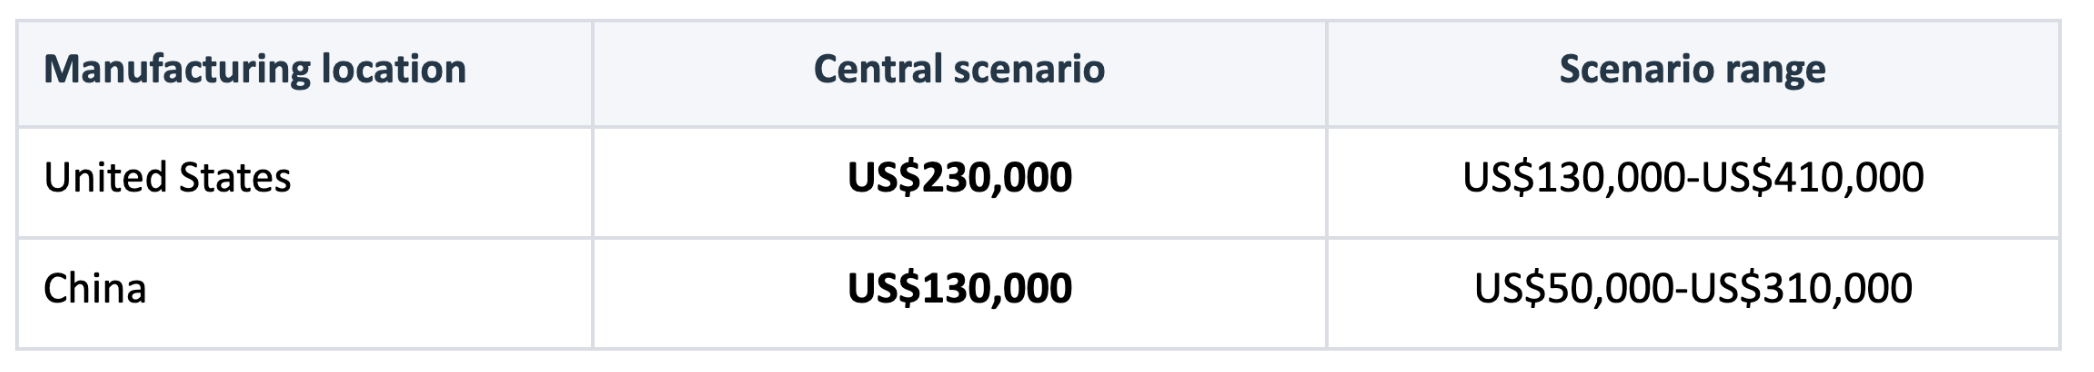
Model status: planning estimate, not reported COGS. Evidence confidence is low-to-moderate for the U.S. central case and low for China.
The U.S. central scenario starts with an estimated US$206,000 attempted-batch subtotal: US$75,000 for GMP IVT inputs, US$40,000 for QC and release, US$25,000 for manufacturing and QA labor, US$20,000 for the patient-specific DNA template, US$18,000 for facility allocation, US$15,000 for LNP formulation and consumables, US$8,000 for fill-finish and packaging, and US$5,000 for dispatch. Dividing by a modeled 90% successful-release probability produces approximately US$229,000 per delivered course. This allocation is illustrative: the public evidence directly anchors the raw-material range, but not every individual cost bucket. The 5%, 10% and 20% repeat-risk assumptions used in the low, central and high scenarios are also modeling inputs—not published industry failure rates.
The U.S. model is anchored against a current commercial disclosure from TriLink, which states that raw materials for a one-patient batch run approximately US$60,000-US$100,000 and that total CDMO charges routinely reach US$300,000-US$500,000. That disclosure is useful, but it is a supplier statement rather than audited cost accounting. The gap between modeled internal cost and CDMO price can include contractor margin, capacity reservation, quality-system overhead and program support. [2]
No comparable audited figure or public China quotation is available. The China scenario therefore applies component-specific multipliers to the U.S. model, informed by official wage data but also by judgment-based assumptions about facility costs and the mix of domestic versus imported inputs. It does not assume reduced GMP standards or fewer release tests. This matters because personalized mRNA products may require assessment of approximately 20-25 critical quality attributes before release. [3-5]
What historical figures can—and cannot—tell us
Historical figures provide useful anchors, but not direct estimates for today's Chinese mRNA PCVs. A 2014 Belgian single-center cost abstract, using hospital data from 2005-2010, reported a preparation cost of €20,450 per patient for a dendritic-cell vaccine used in acute myeloid leukaemia. Provenge, an autologous cellular immunotherapy rather than a neoantigen mRNA PCV, launched in the United States at approximately US$93,000 for a three-infusion course. CMS states that the product payment code included cell collection, activation and other preparatory procedures, while infusion administration was billed separately. Both are nominal historical figures and have not been adjusted for inflation. [7-9]
These examples show that patient-specific therapies carried substantial economic burdens well before today's mRNA PCV programs. They do not validate the US$230,000 or US$130,000 central scenarios: the modalities, dates, care settings and accounting definitions differ, and the Provenge figure is a price rather than COGS.
This is a course-level lot, not a cost per shot
The model does not assume an eight-shot batch. Two prominent regimens illustrate why readers may encounter eight- or nine-dose schedules, but there is no universal course. BioNTech's pancreatic-cancer study used eight intravenous priming doses and one later booster, while Moderna's V940 trials generally administer up to nine doses every three weeks. [10-11]
The manufacturing lot is produced for one patient and contains enough released product for the planned course. Dividing the total by eight or nine produces an accounting figure, not a true per-dose manufacturing cost. Template generation, suite setup, batch records and release testing are incurred once per patient; an additional filled dose often changes cost far less than creating another patient-specific product.
Manufacturing cost is not treatment price
The model excludes biopsy, sequencing, HLA typing, neoantigen prediction, hospital administration, immune monitoring, imaging, combination therapy, R&D recovery and commercial profit. It also excludes the economic cost of patients who progress before receiving a successfully manufactured vaccine. The eventual price paid by a healthcare system could therefore be materially higher than the modeled manufacturing-and-release cost.
The most defensible conclusion is not that one mRNA PCV costs exactly US$230,000 in the United States or US$130,000 in China. It is that six-figure manufacturing cost is a credible central case for today's one-patient process, while the uncertainty remains wide. IVT inputs and patient-level QC limit how much of China's labor and facility advantage can translate into lower cost. For budgeting or procurement, the China figure should be treated as a hypothesis to test against current manufacturer quotations—not as a market price. Audited disclosures or comparable quotations from manufacturers in both markets will be required to narrow the range.
Sources
1. MD Anderson Cancer Genomics Laboratory, Services and Pricing (FY26).
2. TriLink BioTechnologies, Personalized Cancer Vaccine Development.
3. TTP and University of Sheffield, Personalised mRNA Therapies and QC.
4. U.S. Bureau of Labor Statistics, Biological Technicians.
5. National Bureau of Statistics of China, 2025 Annual Wages.
6. Federal Reserve / FRED, Chinese Yuan per U.S. Dollar exchange rate.
8. Reuters, Medicare to Cover Provenge Infusion Costs (2011).
9. CMS, Sipuleucel-T (Provenge) Coverage Criteria and Payment Scope.
11. ClinicalTrials.gov NCT06077760, Intismeran Autogene (V940) dosing schedule.
